


New Approach Methodologies (NAMs): What NIH's Shift Means for Animal Research
New Approach Methodologies (NAMs): What NIH's Shift Means for Animal Research
NIH is expanding investment in human-based research methods. Here is what that means for model selection, the 3Rs, and the animal work that remains scientifically necessary.
TL;DR
NIH is building the infrastructure needed to make human-based research methods more useful and more...
Continue Reading

Astrocytes Are Part of the Circuit: Signaling, Plasticity, and Memory
Astrocytes Are Part of the Circuit: Signaling, Plasticity, and Memory
TL;DR
Astrocytes help maintain the conditions neurons need, but that is only the beginning of the story. They also shape synapses, organize into selective networks, respond to experience, and—in several mouse studies—influence whether a memory can be recalled or maintained. The research...
Continue Reading
The Animal Remembers the Workflow: Why Cumulative Experience Belongs in Study Design
The Animal Remembers the Workflow: Why Cumulative Experience Belongs in Study Design
TL;DR
Cumulative experience looks at the whole study from the animal’s point of view. Repeated mild procedures do not automatically become severe, and animals can habituate to some experiences. But timing, recovery, technique, strain, sex, and individual response can change...
Continue Reading

IACUC Protocols for Rodent Research: What to Include and How to Prepare
IACUC Protocols for Rodent Research: What to Include and How to Prepare
TL;DR
An IACUC protocol describes proposed animal work so the institution can evaluate it before covered activities begin. A useful rodent protocol connects the research question, animal numbers, procedures, and care in one consistent account. Use your institution’s current form...
Continue Reading
RFID Microchips for Mice and Rats: A Guide to Rodent Identification
RFID Microchips for Mice and Rats: A Guide to Rodent Identification
TL;DR
RFID microchips give research mice and rats an electronic identifier that a compatible reader can retrieve. They are worth considering when the same animal moves through repeated procedures, measurements, or staff handoffs. Their usefulness depends on how reliably the scan...
Continue Reading

Laboratory Animal Management: Building Better Rodent Research Workflows
Laboratory Animal Management: Building Better Rodent Research Workflows
TL;DR
Laboratory animal management connects daily care with the people, procedures, and records that support a study. For mice and rats, the practical goal is continuity: the approved plan should remain clear as an animal moves from housing through a procedure and recovery. Reliable...
Continue Reading
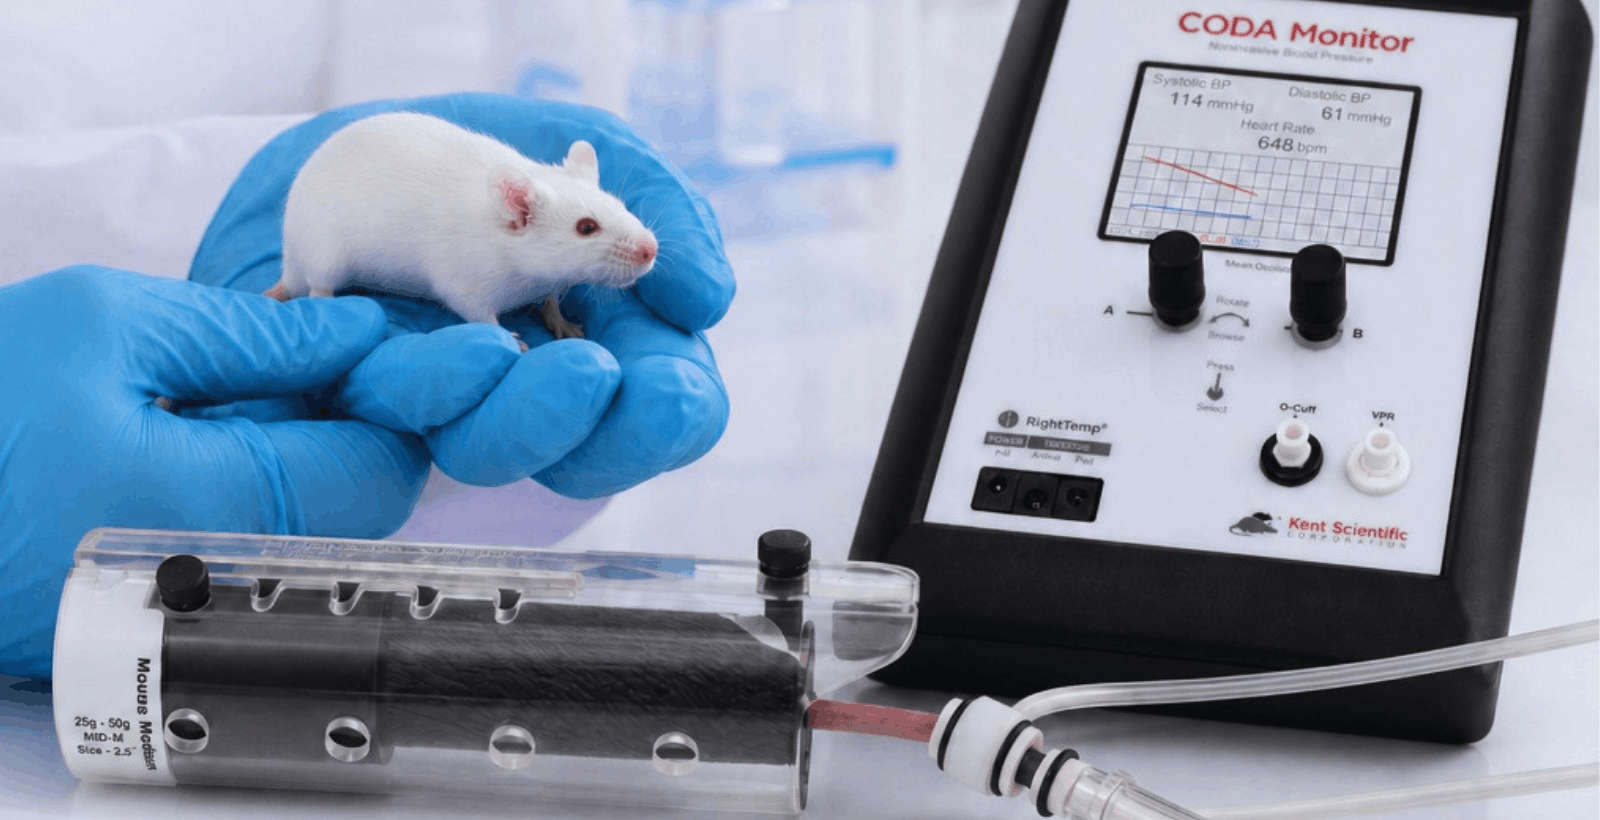
CODA vs. Other Rodent Blood Pressure Systems: How to Compare Tail-Cuff Options
CODA vs. Other Rodent Blood Pressure Systems: How to Compare Tail-Cuff Options
TL;DR
The closest alternatives to the CODA® High Throughput System are the Hatteras MC4000, Visitech BP-2000, and IITC MRBP because each supports multi-animal, non-invasive tail-cuff blood pressure measurement in mice and rats. Panlab can accommodate multiple restrained animals, but its measurements...
Continue Reading

Rat as a Model Organism: Advantages, Limitations, and When to Use Rats in Research
Rat as a Model Organism: Advantages, Limitations, and When to Use Rats in Research
TL;DR Why are rats used as model organisms?
Rats are used as model organisms because their physiology, behavior, body size, and well-characterized genetics make them useful for studying complex biological systems and human disease. Compared with mice, their...
Continue Reading

Tail-Cuff vs. Telemetry: How to Choose Based on Study Design
Tail-Cuff vs. Telemetry: How to Choose Based on Study Design
TL;DR
Choose tail-cuff when your study needs scheduled blood pressure measurements across multiple mice or rats without surgical implantation. Choose telemetry when continuous, beat-to-beat, circadian, or freely moving measurements are essential to the hypothesis. Neither method is universally better. The right choice...
Continue Reading
How to Reduce Waste Anesthetic Gas in Rodent Workflows
How to Reduce Waste Anesthetic Gas in Rodent Workflows
TL;DR
To reduce waste anesthetic gas in rodent workflows, start at the source: use an appropriate fresh gas flow for the animal and procedure, connect and maintain an effective scavenging system, check the anesthesia circuit for leaks, limit gas release during induction and...
Continue Reading

Guide to Green Anesthesia in Research Labs
Guide to Green Anesthesia in Research Labs
Practical ways to reduce waste gas, cost, and environmental impact in rodent workflows
TL;DR
Green anesthesia in research labs is about reducing avoidable waste while still delivering appropriate anesthesia for the animal and procedure. In rodent workflows, that usually starts with flow rate, waste anesthetic gas...
Continue Reading

Traditional vs. Integrated Digital: How to choose Anesthetic Vaporizers
Traditional vs. Integrated Digital: How to choose Anesthetic Vaporizers
Why Size-Appropriate Anesthesia Matters for Animal Safety
TL;DR:
Traditional vaporizers are familiar and widely used, but they are often run at flow rates above what mice and rats need. Integrated digital anesthetic vaporizers are designed to make small animal anesthesia more size-appropriate, with lower...
Continue Reading